Sildenafil for Erectile Dysfunction in Europe: Treatment Options, Strengths and Safety


Sildenafil for Erectile Dysfunction in Europe: Treatment Options, Strengths, and Safety Guidelines
Critical Cardiovascular & Regulatory Safety Notice
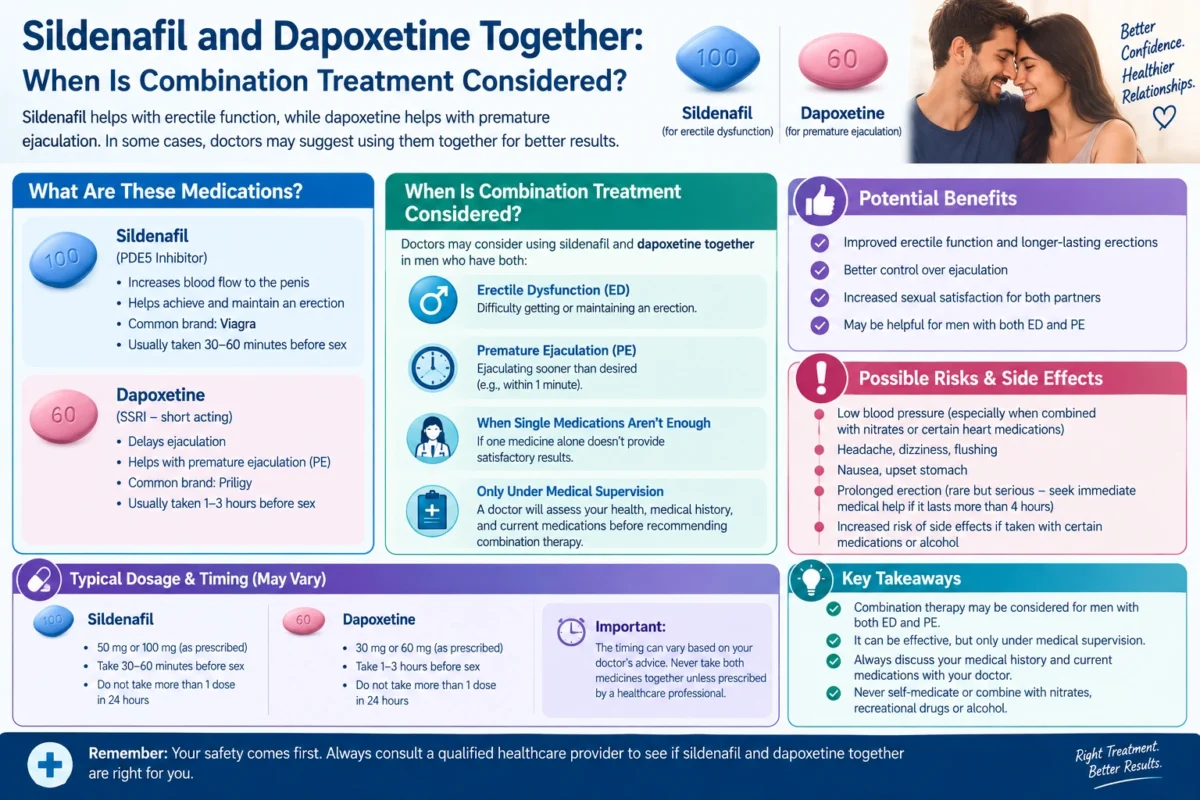
Sildenafil is a selective phosphodiesterase type 5 (PDE5) inhibitor indicated for the treatment of erectile dysfunction (ED) in adult men. Across European jurisdictions (regulated by the EMA and national agencies like the MHRA, BfArM, and ANSM), Sildenafil is available under prescription or via pharmacist-led behind-the-counter schemes (e.g., Pharmacy-P / OTC in select countries). Co-administration of Sildenafil with organic nitrates (such as nitroglycerin or isosorbide) or guanylate cyclase stimulators (such as riociguat) is strictly contraindicated due to the risk of severe, fatal hypotension. Men with underlying cardiovascular disease must undergo medical evaluation before initiating therapy. This guide serves strictly educational purposes.
Erectile dysfunction (ED)—the persistent inability to achieve or maintain a penile erection sufficient for satisfactory sexual performance—affects an estimated 30 million men across Europe. While often perceived as a localized sexual health issue, ED is frequently an early clinical marker of broader systemic vascular conditions, including endothelial dysfunction, atherosclerosis, and hypertension.
First approved by the European Medicines Agency (EMA) in 1998, **Sildenafil Citrate** remains the foundational, gold-standard oral first-line therapy for erectile dysfunction throughout European clinical practice.
Navigating Sildenafil therapy in Europe requires understanding its physiological mechanism of action, the therapeutic spectrum of available dosage strengths, clinical distinctions between on-demand and low-dose daily protocols, essential cardiovascular safety rules, and proper administration practices.
Mechanism of Action: How Sildenafil Restores Penile Hemodynamics
Penile erection is a hemodynamic process governed by autonomic neurovascular signaling. Sexual stimulation triggers the local synthesis and release of nitric oxide (NO) from non-adrenergic, non-cholinergic (NANC) nerves and endothelial cells within the corpus cavernosum.
The NO-cGMP Pathway Modulation
1. Guanylate Cyclase Activation: Nitric oxide diffuses into vascular smooth muscle cells, activating the cytoplasmic enzyme soluble guanylate cyclase (sGC), which converts GTP into cyclic guanosine monophosphate (cGMP).
2. Smooth Muscle Relaxation & Engorgement: Elevated intracellular cGMP promotes calcium efflux, relaxing the trabecular smooth muscle and cavernous helicine arteries. This allows rapid arterial inflow and corporal veno-occlusion, generating a rigid erection.
3. Competitive PDE5 Inhibition: Under normal physiology, the enzyme phosphodiesterase type 5 (PDE5) rapidly degrades cGMP, returning the tissue to a flaccid state. Sildenafil acts as a potent, competitive, and reversible inhibitor of PDE5. By preventing cGMP breakdown, it amplifies and sustains natural erectile responses during sexual arousal.
Because Sildenafil depends strictly on upstream nitric oxide release, it does not induce an involuntary erection; appropriate sensory and mental sexual stimulation is mandatory for therapeutic efficacy.
European Treatment Options and Dosage Strengths
Across the European Union and the United Kingdom, Sildenafil is manufactured in diverse strengths to accommodate varying clinical severities, patient ages, hepatic clearances, and treatment strategies:
1. Standard On-Demand Formulations (25 mg, 50 mg, 100 mg)
- 50 mg (Standard Starting Dose): The recommended initial on-demand dose for most adult men, taken approximately 30 to 60 minutes before sexual intercourse.
- 100 mg (Maximum Single Dose): Prescribed when the 50 mg strength yields insufficient erectile rigidity in the absence of troublesome adverse reactions (frequently used in diabetic or post-surgical populations).
- 25 mg (Low Starting Dose): Indicated for elderly patients (≥65 years), individuals with mild-to-moderate hepatic impairment or severe renal impairment, or patients co-administered potent CYP3A4 inhibitors.
2. Low-Dose Daily Protocols (20 mg Micro-Dosing)
While originally registered under pulmonary arterial hypertension (PAH) indications, micro-dose formulations—such as Sildenafil Citrate Tablets 20 Mg—are increasingly evaluated by European urologists for off-label daily endothelial rehabilitation, nocturnal penile tumescence recovery post-radical prostatectomy, and customized micro-titration regimens.
Clinical Overview Matrix
The table below summarizes the key pharmacological parameters, standard European dosing tiers, and safety monitoring rules for Sildenafil Citrate:
| Clinical Parameter | Pharmacological Detail | European Practice & Safety Guidelines |
|---|---|---|
| Therapeutic Class | Selective PDE5 Inhibitor (Vasodilator) | First-line oral monotherapy (European Association of Urology – EAU Guidelines). |
| Onset & Duration | Onset: 30–60 mins; Duration: 4–6 hours | Absorption is significantly delayed by heavy or high-fat meals. |
| Available Doses | 20 mg, 25 mg, 50 mg, 100 mg | Maximum dosing frequency is strictly once within a 24-hour window. |
| Metabolic Pathway | Hepatic CYP3A4 (major) and CYP2C9 (minor) | Dose reduction required when co-prescribed with ketoconazole, erythromycin, or ritonavir. |
Optimizing Administration: Maximizing Clinical Success
Clinical non-response to Sildenafil often results from incorrect administration rather than true pharmacological failure. European urological guidelines recommend attempting at least 4 to 8 distinct dosing trials before classifying a patient as a non-responder:
- Fasting vs. Fed State: Take Sildenafil on an empty stomach or after a light meal. Co-ingestion with high-fat meals delays gastric emptying, prolonging the time to peak plasma concentration ($T_{\max}$) by over an hour and reducing peak plasma levels ($C_{\max}$) by nearly 30%.
- Adequate Timing: Ingest the tablet 30 to 60 minutes prior to intimacy with a full glass of water.
- Alcohol Moderation: Excessive alcohol consumption impairs central nervous system erectile reflexes and increases the risk of orthostatic lightheadedness. Keep alcohol intake minimal during treatment.
- Address Psychological Context: Performance anxiety can trigger sympathetic alpha-adrenergic surges that override PDE5-mediated smooth muscle relaxation.
Adverse Effects, Contraindications, and Cardiovascular Safety
Sildenafil is broadly well-tolerated, but its systemic vasodilatory properties require strict adherence to clinical boundaries:
Adverse Reactions and Critical Contraindications
1. Common Mild Side Effects: Transient headache (~16%), facial flushing (~10%), dyspepsia, nasal congestion, and mild visual tinting/photophobia (caused by mild cross-inhibition of PDE6 in retinal photoreceptors).
2. Absolute Nitrate Contraindication: Co-administration with short- or long-acting organic nitrates (e.g., nitroglycerin sublingual spray, isosorbide mononitrate) or recreational alkyl nitrites (“poppers”) can trigger life-threatening systemic vasodilation and circulatory collapse. A minimum 24-hour washout period is mandatory between Sildenafil ingestion and any urgent nitrate administration.
3. Alpha-Blocker Separation: When co-prescribed with alpha-blockers for hypertension or benign prostatic hyperplasia (BPH) (such as tamsulosin or doxazosin), patients should be hemodynamically stable on their alpha-blocker regimen prior to initiating Sildenafil at the lowest 25 mg dose to avoid symptomatic orthostatic hypotension.
4. Priapism & Ocular Emergencies: Prolonged erections lasting longer than 4 hours (priapism) require immediate emergency urological intervention to prevent irreversible fibrosis of the erectile tissue. Sudden loss of vision—indicative of Non-Arteritic Anterior Ischemic Optic Neuropathy (NAION)—requires immediate drug discontinuation.
For an exhaustive, peer-reviewed database detailing the chemical structure, molecular mechanics, and clinical trials of Sildenafil Citrate, consult the official National Center for Biotechnology Information (NCBI) PubChem Database.
For pan-European clinical guidelines and regulatory directives on cardiovascular and men’s health therapeutics, visit the official World Health Organization (WHO) Health Directory.
Sildenafil European Treatment Safety Checklist
Keep these core clinical guidelines in mind when evaluating or undertaking treatment:
- ✔️ Undergo a Cardiovascular Assessment: Ensure a medical professional screens your cardiovascular health and exercise tolerance before starting therapy.
- ✔️ Never Combine with Nitrates: Confirm that you are not taking nitrate medications or guanylate cyclase stimulators.
- ✔️ Take on an Empty Stomach: Avoid heavy, high-fat meals before dosing to ensure rapid, predictable absorption.
- ✔️ Allow for Sexual Arousal: Remember that mental or tactile sexual stimulation is necessary for the drug to work.
- ✔️ Do Not Exceed One Dose Daily: Never take more than one prescribed dose within a 24-hour period.