Restasis 0.05% Ophthalmic Emulsion (0.4 ml) – Calcineurin Inhibitor for Chronic Dry Eye
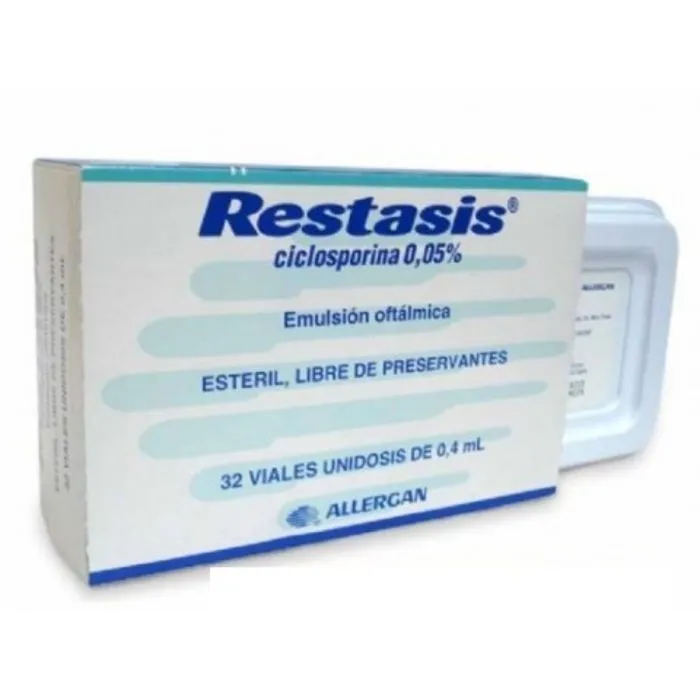
Restasis 0.05% Ophthalmic Emulsion (0.4 ml) is a preservative-free topical immunomodulator containing cyclosporine, indicated to increase natural tear production in patients whose tear production is presumed to be suppressed due to ocular inflammation associated with keratoconjunctivitis sicca (chronic dry eye disease). By inhibiting calcineurin-mediated T-cell activation, it restores ocular surface immune homeostasis to promote sustained, endogenous tear flow.
Cyclosporine 0.05%
Single-Use Vials (0.4 ml)
Calcineurin Inhibitor Immunomodulator
Preservative-Free Ophthalmic
Active Ingredient
Cyclosporine (0.05% w/v)
Unit Pack Size
0.4 ml Single-Use Vial
Therapeutic Class
Topical Calcineurin Inhibitor Immunosuppressant
Dosage Form
Sterile Preservative-Free Ophthalmic Emulsion
What Is Restasis 0.05% Ophthalmic Emulsion?
Restasis 0.05% is an ophthalmic emulsion supplied in single-use 0.4 ml preservative-free plastic vials. It contains cyclosporine, a cyclic polypeptide immunosuppressant that targets the underlying autoimmune inflammatory cycle responsible for chronic keratoconjunctivitis sicca (dry eye disease).
Unlike traditional artificial tears that merely provide transient symptomatic surface lubrication, Restasis is a disease-modifying topical therapy. It addresses chronic inflammatory damage within the lacrimal glands and conjunctival tissue, stimulating the patient’s own ocular tissues to resume endogenous aqueous tear production.
Restasis is formulated for long-term daily management. Because it acts at the level of cellular immune modulation, therapeutic improvements typically build gradually, with meaningful increases in tear volume observable over several weeks to months of continuous compliance.
([dailymed.nlm.nih.gov](https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=a00e5ba6-df27-4a00-bebe-8dfda8537b01))
How Does Restasis 0.05% Work?
In chronic dry eye syndrome, activated CD4+ T-lymphocytes infiltrate the lacrimal glands and ocular surface, releasing pro-inflammatory cytokines that disrupt neural signaling and suppress aqueous tear production:
- Cyclophilin Binding: Intracellularly, cyclosporine binds to its cytoplasmic receptor protein, cyclophilin, to form an active immunosuppressive complex.
- Calcineurin Phosphatase Inhibition: This drug-protein complex binds and inhibits calcineurin, a calcium/calmodulin-dependent phosphatase essential for dephosphorylating the Nuclear Factor of Activated T-cells (NF-AT).
- Suppression of Cytokine Transcription: By preventing NF-AT translocation into the nucleus, cyclosporine halts the transcription and secretion of pro-inflammatory cytokines—chiefly interleukin-2 (IL-2), interferon-gamma (IFN-γ), and tumor necrosis factor-alpha (TNF-α).
- Lacrimal Gland Functional Recovery: Halting T-cell mediated ocular surface inflammation reduces apoptosis in conjunctival goblet cells and restores neurosecretory signaling, allowing the lacrimal functional unit to produce natural tears.
Because cyclosporine acts as an immunomodulator rather than a general vasoconstrictor or broad corticosteroid, it suppresses targeted inflammatory pathways without increasing intraocular pressure or inducing cataract formation.
What Is Restasis 0.05% Used For?
Restasis is clinically approved for increasing tear production in specific inflammatory ocular conditions:
- Chronic Keratoconjunctivitis Sicca (Dry Eye Disease): Patients whose natural tear secretion is diminished due to underlying ocular surface inflammation.
- Sjögren’s Syndrome-Associated Dry Eye: Long-term management of autoimmune lacrimal gland hypofunction under ophthalmic supervision.
- Corneal Epithelial Erosion Prevention: Preservation of corneal surface integrity in chronic severe dry eye unresponsive to tear substitutes alone.
- Conjunctival Goblet Cell Recovery: Promotion of mucin-layer stability by restoring conjunctival epithelial goblet cell density.
Increased tear production is not typically observed in patients currently using topical anti-inflammatory drugs (such as corticosteroids) or in individuals with mechanical lacrimal gland obstruction or punctal plug closure.
([dailymed.nlm.nih.gov](https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=a00e5ba6-df27-4a00-bebe-8dfda8537b01))
Related Ocular Surface Therapy
While Restasis targets chronic autoimmune tear-deficiency and lacrimal inflammation, allergic ocular itching, redness, and swelling require dual-action antihistamine and mast-cell stabilizing agents. Explore our clinical review of Pataday:
Pataday Eye Drop (Olopatadine Hydrochloride)
Restasis 0.05% Dosage and Administration Guidelines
Aseptic technique and proper preparation ensure correct delivery of the emulsion:
- Standard Dosing: Instill 1 drop into each affected eye twice daily, approximately 12 hours apart.
- Emulsion Preparation: Invert the single-use vial several times prior to opening to obtain a uniform, white, opaque emulsion.
- Immediate Single-Use Application: Open the vial by twisting off the tab. Instill the drop immediately into the conjunctival sac. Discard the vial and any remaining contents immediately after application; single-use vials contain no antimicrobial preservatives.
- Spacing with Artificial Tears: Restasis can be used concomitantly with lubricating artificial tears, provided administrations are separated by at least 15 minutes.
To preserve sterile conditions, do not allow the vial tip to touch the eye surface, fingers, or surrounding skin.
([dailymed.nlm.nih.gov](https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=a00e5ba6-df27-4a00-bebe-8dfda8537b01))
Important Contact Lens Guidance:
Patients with decreased tear production should generally avoid wearing contact lenses. If contact lenses are worn, remove them prior to instillation of Restasis and wait at least 15 minutes before reinsertion.
Restasis 0.05% vs Pataday Eye Drops (Olopatadine)
Comparing a chronic immunomodulatory emulsion with an acute antiallergic agent clarifies their distinct clinical mechanisms and treatment goals:
| Clinical Parameter |
Restasis 0.05% (Cyclosporine) |
Pataday Eye Drops (Olopatadine) |
| Pharmacological Class |
Calcineurin inhibitor immunomodulator |
Histamine H1 antagonist / Mast-cell stabilizer |
| Primary Indication |
Suppressed tear production (Keratoconjunctivitis sicca) |
Ocular itching & redness from allergic conjunctivitis |
| Onset of Action |
Gradual therapeutic onset (typically 4 to 12 weeks) |
Rapid relief within minutes of instillation |
| Dosing Schedule |
Twice daily (spaced 12 hours apart) |
Once daily or twice daily (concentration-dependent) |
| Preservative Status |
Preservative-free single-use unit vials |
Multi-dose bottle preserved with Benzalkonium Chloride |
Restasis is indicated for ongoing immune-mediated tear deficiency, whereas Pataday provides fast, targeted relief for allergen-driven itching and histamine flares.
Who Should Not Use Restasis 0.05%?
Restasis is contraindicated or requires caution in patients with the following conditions:
- Known hypersensitivity or allergic reaction to cyclosporine or any excipients in the emulsion (castor oil, polysorbate 80, carbomer copolymer)
- Active ocular infections (viral, bacterial, or fungal keratitis or conjunctivitis); local immunomodulation may compromise host anti-infective clearance
- Children under 16 years of age (safety and efficacy have not been established in pediatric keratoconjunctivitis sicca)
- Use while wearing contact lenses during active ocular surface inflammation
- Pregnancy and nursing (use only if explicitly determined essential by an obstetrician and ophthalmologist)
Careful ophthalmic evaluation is recommended for patients with a history of herpes simplex keratitis prior to starting calcineurin inhibitor drops.
([dailymed.nlm.nih.gov](https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=a00e5ba6-df27-4a00-bebe-8dfda8537b01))
Possible Side Effects of Restasis
Systemic absorption of cyclosporine following topical ocular administration is negligible, and adverse events are largely localized to the ocular surface:
- Ocular Burning & Stinging: The most common adverse effect (reported in ~17% of patients), typically occurring immediately after drop instillation and subsiding as the ocular surface heals over weeks.
- Conjunctival Hyperemia: Mild transient redness or vascular injection of the sclera.
- Epiphora & Ocular Discharge: Temporary reflex tearing or sticky ocular discharge.
- Visual Effects: Transient blurring of vision immediately following administration due to the thick emulsion vehicle.
- Foreign Body Sensation: Grittiness, ocular pain, pruritus, or stinging.
If severe, persistent eye pain, worsening corneal erosion, or signs of ocular infection emerge, contact an eye specialist immediately.
([dailymed.nlm.nih.gov](https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=a00e5ba6-df27-4a00-bebe-8dfda8537b01))
Drug Interactions and Co-Administration Guidelines
Blood concentrations of cyclosporine following topical administration of Restasis remain below the limit of clinical assay quantification (< 0.1 ng/mL), eliminating systemic cytochrome P450 interactions:
Separation from Artificial Tears: If non-medicated artificial tears or lubricating gels are used, separate instillations by at least 15 minutes to prevent the tear substitute from diluting or washing away the cyclosporine emulsion.
Topical Ophthalmic Steroids: Concomitant use with topical corticosteroids may be used temporarily as a bridge to reduce early stinging or acute inflammation, but long-term combination requires careful monitoring of intraocular pressure.
([dailymed.nlm.nih.gov](https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=a00e5ba6-df27-4a00-bebe-8dfda8537b01))
Preservative-Free Vial Handling & Storage
Restasis 0.4 ml unit-dose vials are completely preservative-free, avoiding benzalkonium chloride toxicity in already compromised dry eyes:
Each vial contains enough emulsion to dose both eyes once. Once opened, the vial must be discarded immediately after use, even if liquid remains. Attempting to save open vials for subsequent doses exposes the solution to bacterial and fungal contamination. Store unopened vials in their original foil pouch at controlled room temperature ($15^\circ\text{C to }25^\circ\text{C}$).
Treatment Timeline & Clinical Expectations
Because Restasis works through immunomodulation of the lacrimal functional unit, clinical improvements follow a gradual trajectory:
Weeks 1–4 (Initial Phase): Patients may experience transient burning or stinging upon instillation. Tear production is typically unchanged during this early phase; concurrent artificial tears help maintain surface comfort.
Weeks 6–12 (Early Objective Response): Ocular surface inflammation declines, conjunctival staining scores improve, and early increases in natural tear volume can be measured via Schirmer testing.
Months 3–6 (Sustained Improvement): Peak therapeutic increases in natural tear production, goblet cell density restoration, and symptom relief are generally achieved with continuous, uninterrupted twice-daily therapy.
([dailymed.nlm.nih.gov](https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=a00e5ba6-df27-4a00-bebe-8dfda8537b01))
Frequently Asked Questions About Restasis 0.05%
1. How long does it take for Restasis to start working?
Restasis does not provide immediate relief like lubricating drops. Because it acts on underlying cellular inflammation, noticeable improvements in natural tear production and symptom relief typically develop gradually over 4 to 12 weeks, with peak benefits seen around 3 to 6 months of continuous twice-daily use.
([dailymed.nlm.nih.gov](https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=a00e5ba6-df27-4a00-bebe-8dfda8537b01))
2. Is burning or stinging normal after instilling Restasis?
Yes. Ocular burning and stinging is the most common adverse reaction, reported in roughly 17% of patients. It occurs primarily during early weeks of therapy when the ocular surface is inflamed and typically diminishes as the corneal epithelial barrier heals with continued use.
3. Can I save the leftover Restasis liquid in the vial for the evening dose?
No. Restasis vials are preservative-free and strictly designed for single-use application. Once opened, the vial must be discarded immediately after dosing both eyes, as unpreserved solutions are susceptible to rapid bacterial colonization.
4. Can I use artificial tears while taking Restasis?
Yes. Lubricating drops may be used concurrently to provide immediate surface comfort while Restasis builds natural tear production. Ensure you space artificial tears and Restasis by at least 15 minutes to avoid diluting the cyclosporine emulsion.
([dailymed.nlm.nih.gov](https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=a00e5ba6-df27-4a00-bebe-8dfda8537b01))
5. What is the difference between Restasis and Pataday?
Restasis is an immunomodulating cyclosporine emulsion used long-term to increase tear production in chronic dry eye disease. Pataday is an antihistamine and mast-cell stabilizer (olopatadine) used to relieve acute itching, redness, and swelling caused by ocular allergies.
Medical Disclaimer
This product overview is provided strictly for educational and informational purposes. Restasis 0.05% Ophthalmic Emulsion (cyclosporine) is a prescription ophthalmic medication that must only be initiated, dosed, and monitored under the care of a licensed ophthalmologist or optometrist. Individual therapeutic response, tolerance, and underlying ocular surface disease etiology require specialized clinical evaluation. This document does not replace professional medical evaluation, clinical diagnosis, or personalized ophthalmic management.











Reviews
There are no reviews yet.